
A new breast cancer diagnosis brings a flood of unfamiliar terms: breast conservation surgery, lumpectomy, neoadjuvant chemotherapy, clear margins, oncoplastic surgery, sentinel lymph node biopsy. Understanding what these terms generally mean can help you take an active role in discussing treatment with your breast cancer team.
This guide brings together 15 of the most commonly searched, highest-interest questions patients ask across five key areas of breast-conserving cancer care: general breast conservation surgery, chemotherapy before surgery, surgical technique and margins, oncoplastic breast reshaping and reconstruction, and sentinel lymph node biopsy. Each answer opens with a clear, general statement and is followed by practical detail, so you can prepare informed questions for your own surgeon.
A note on how to read this guide: Statistics, timelines and outcomes below reflect patterns reported in published research and general clinical practice; they describe groups of patients, not guarantees for any individual. Words such as “usually,” “typically” and “in most cases” are used deliberately, because your own tumour biology, stage, general health and treatment response may change what applies to you.
In this guide: Breast conservation surgery | Chemotherapy before surgery | Technique, margins and localisation | Oncoplastic surgery | Sentinel lymph node biopsy | Key takeaways and timeline. See also our Breast – Oncoplastic Surgery page.
Most women diagnosed with early-stage breast cancer are able to keep their breast through breast conservation surgery (lumpectomy), which removes only the tumour and a surrounding rim of healthy tissue rather than the entire breast.
Whether breast conservation is suitable for you depends on individual factors your surgeon will assess, including the size of the tumour relative to your breast, whether the cancer is confined to one area, and whether radiotherapy is safe for you. Chemotherapy before surgery and oncoplastic reshaping techniques have expanded eligibility for many patients who previously would have been offered mastectomy first.
Your surgeon will typically weigh up the following when discussing your options:
Current evidence from decades of large randomised trials shows that breast conservation surgery combined with radiotherapy achieves overall survival that is generally comparable to mastectomy for eligible patients with early-stage breast cancer.
These figures describe average outcomes across large groups of patients studied over many years; your own risk depends on tumour type, grade, stage and how your cancer responds to treatment, which is why individual prognosis is discussed separately with your oncology team.
| Outcome | Lumpectomy + radiotherapy | Mastectomy |
|---|---|---|
| Overall survival, early-stage disease | Generally comparable | Generally comparable |
| Local recurrence at 10 years | Typically low single digits, with radiotherapy | Somewhat lower on average, without a survival benefit |
| Radiotherapy required | In most cases | Only in selected higher-risk cases |
| Breast tissue preserved | Yes, in most of the breast | No (reconstruction is an option) |
In short, the decision between these two operations is generally about extent of surgery, recovery and appearance rather than a meaningful difference in survival for most eligible patients — but this should always be confirmed against your own pathology report.
You are typically considered a reasonable candidate for breast conservation surgery if your cancer is confined to one area, can likely be removed with clear margins, and you are able to have radiotherapy; you are usually advised against it if the disease is widespread or radiotherapy cannot be safely given.
As a general guide, surgeons commonly distinguish candidates as follows:
These categories are general patterns, not fixed rules — your own suitability should always be confirmed directly with your breast surgeon.
Neoadjuvant chemotherapy is cancer treatment given before surgery to shrink the tumour, and in many cases it can allow patients who would otherwise need a mastectomy to become candidates for breast-conserving surgery instead.
This approach tends to be most effective in triple-negative and HER2-positive breast cancers, where tumours often shrink substantially or, in some patients, disappear entirely on later imaging. Current research indicates that survival outcomes are generally similar whether the same chemotherapy is given before or after surgery, though this should be confirmed for your specific cancer subtype.
Neoadjuvant chemotherapy is generally recommended for triple-negative and HER2-positive cancers larger than about 2 cm or with lymph node involvement, and for locally advanced cancers that are not initially safe to operate on.
Response rates vary considerably by cancer subtype, as summarised here:
| Cancer subtype | Typical approach | Reported chance tumour fully disappears |
|---|---|---|
| Triple-negative | Chemotherapy, often combined with immunotherapy | Roughly 40 to 65% in published series |
| HER2-positive | Chemotherapy plus HER2-targeted drugs | Roughly 50 to 65% in published series |
| Hormone-positive, HER2-negative | Chemotherapy generally reserved for higher-risk cases | Typically under 10% |
These are population-level figures from clinical studies; your individual response cannot be predicted with certainty in advance and will be monitored with imaging during treatment.
A small metal marker clip is usually placed in the tumour before chemotherapy so your surgeon can reliably find and remove the correct area later, even if the cancer shrinks or appears to disappear on scans.
This simple, low-risk step generally serves several purposes:
Clear (negative) margins generally mean no cancer cells are found at the outer edge of the tissue removed, and achieving them is widely regarded by breast surgeons as the most important technical factor in reducing the risk of the cancer returning in the breast.
Current consensus guidelines define acceptable margins as follows:
| Cancer type | Generally accepted clear margin |
|---|---|
| Invasive breast cancer | No cancer cells touching the inked edge (“no ink on tumour”) |
| DCIS (non-invasive, ductal carcinoma in situ) | 2 mm or more of healthy tissue, per current consensus guidance |
| After chemotherapy before surgery | No ink on any remaining tumour |
Based on current research, margins wider than these thresholds have not been shown to further lower recurrence risk, so most surgeons aim for margins that are clear rather than maximal — though your surgeon may adapt this to your specific pathology.
A positive margin means cancer cells reach the edge of the removed tissue, and this typically leads to a second, smaller operation (re-excision) to remove the remaining tissue, a scenario reported in roughly 10 to 20% of lumpectomies in published series.
If this happens, the general sequence of events is usually as follows:
Needing a second procedure does not necessarily indicate a worse prognosis; it reflects the microscopic extent of disease found on pathology, which cannot always be predicted before surgery.
When a tumour cannot be felt by hand, it is typically located precisely before or during surgery using a guide wire, radioactive seed, magnetic seed or radar reflector, helping ensure that only the intended area is removed.
Several localisation methods are commonly used, each with its own advantages:
| Localisation method | How it generally works | Typical advantage |
|---|---|---|
| Wire localisation | A thin wire is placed on the day of surgery | Widely available in most centres |
| Radioactive or magnetic seed | A tiny marker is placed days beforehand | Allows more flexible scheduling |
| Radar reflector / ultrasound guidance | Detected by a probe or seen directly on ultrasound | Avoids radiation exposure |
After removal, the tissue specimen is usually X-rayed in the operating room to help confirm that the tumour and any marker have been captured, though final confirmation always comes from formal pathology.
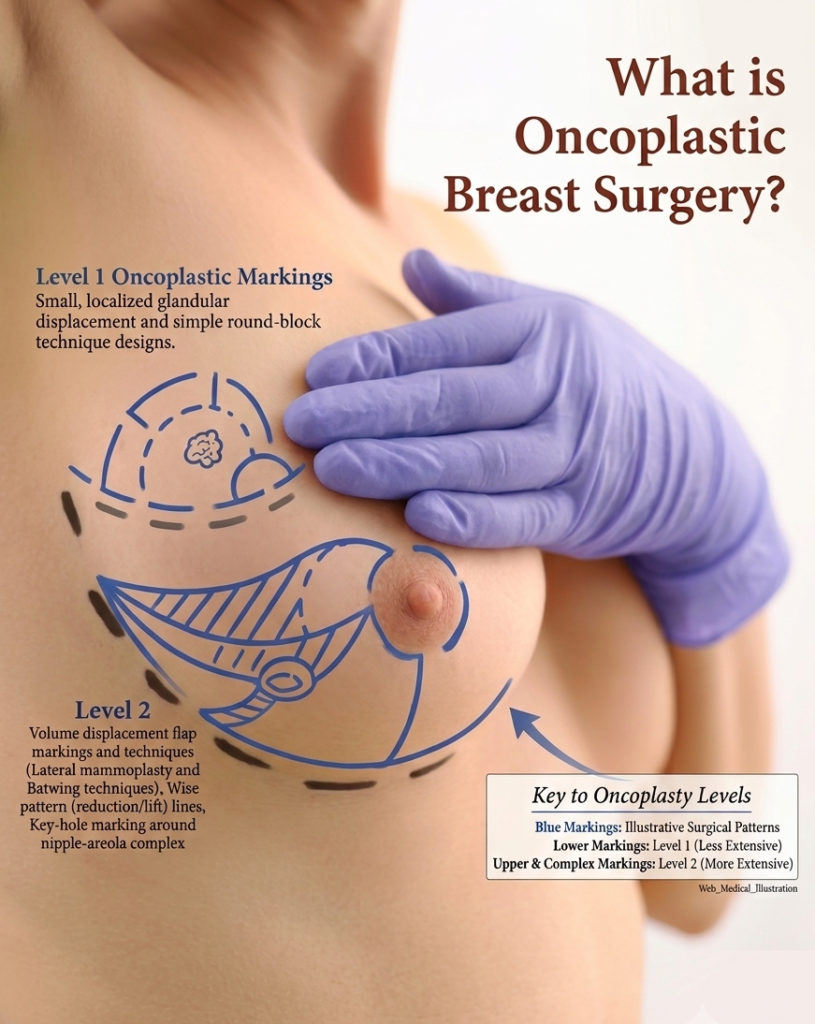
Oncoplastic breast surgery combines cancer removal with plastic surgery reshaping techniques in the same operation, and it is generally used to allow larger tumours to be removed while aiming to preserve a natural breast shape, in contrast to a standard lumpectomy, which typically closes the resulting gap directly.
This approach tends to give surgeons more room to take adequately wide margins with greater confidence, and published outcome data generally suggest cancer control comparable to standard breast-conserving surgery, alongside improved cosmetic results on average — though individual results vary with tumour size, breast size and technique used.
Oncoplastic techniques are generally grouped into Level I procedures (removing under about 20% of breast volume) and Level II procedures (roughly 20 to 50%), with the specific pattern usually chosen according to where the tumour is located in the breast.
As a general reference, commonly used techniques by location include:
| Tumour location | Typically used oncoplastic technique |
|---|---|
| Upper breast | Round block (donut), batwing, radial ellipse |
| Lower pole | Inverted-T (Wise pattern), J-plasty |
| Behind the nipple (central) | Grisotti flap, central excision with nipple reconstruction |
| Large or lower, drooping breast | Therapeutic mammoplasty (reduction pattern) |
When comparatively little breast tissue remains after removal, a “volume replacement” flap of tissue from the back or side chest wall may be used instead of rearranging the breast itself — the final choice is generally made in the operating room based on what is found.
Oncoplastic surgery carries a low but real risk of complications, reported at roughly 10 to 20% of patients in published series, most commonly delayed wound healing, fat necrosis or asymmetry, and surgery on the opposite breast (symmetrisation) is optional, offered to help match its size and shape.
Commonly reported complications, in approximate order of frequency, include:
As with any cancer surgery, individual complication risk depends on factors such as smoking status, breast size, diabetes and the extent of tissue removed, and should be discussed directly with your surgical team.
Sentinel lymph node biopsy removes and examines the first one to three lymph nodes that drain the breast, to check whether breast cancer has spread to the armpit, and it is generally regarded as the standard, minimally invasive alternative to removing all the armpit lymph nodes when nodes feel normal before surgery.
For most patients, this approach provides accurate cancer staging while typically causing significantly less arm swelling, numbness and shoulder stiffness than removing all the lymph nodes, and it is usually performed during the same operation as breast surgery.
Not necessarily: for many women with only one or two positive sentinel lymph nodes who are having breast conservation surgery and radiotherapy, current evidence suggests full removal of all armpit lymph nodes can often be safely avoided.
This shift in practice is based on several major clinical trials, summarised below:
| Trial | General finding |
|---|---|
| ACOSOG Z0011 | Reported equivalent survival without full node clearance in selected patients with 1–2 positive sentinel nodes |
| AMAROS | Found armpit radiotherapy an effective alternative to full clearance, with less arm swelling |
| SENOMAC | Supported omitting full clearance in selected patients with limited nodal disease |
Based on these findings, your team may instead recommend armpit radiotherapy or close monitoring rather than full clearance; more extensive nodal disease, however, is still generally treated with full lymph node removal.
Sentinel lymph node biopsy is generally considered a low-risk procedure, with a reported lymphoedema (arm swelling) rate of around 5%, compared with roughly 15 to 30% after full axillary lymph node clearance.
For logistics and planning purposes, the two procedures generally compare as follows:
| Consideration | Sentinel node biopsy | Full axillary clearance |
|---|---|---|
| Reported lymphoedema risk | About 5% | About 15 to 30% |
| Numbness or shoulder stiffness | Generally less common | Generally more common |
| Typical recovery time | A few days | Several weeks |
A few general precautions are commonly recommended to reduce lymphoedema risk after either procedure:
Key takeaways
The following overview reflects a commonly reported sequence of care; the exact order and duration can vary by hospital, cancer subtype and individual treatment plan.
| Stage | What it generally involves | Typical timing |
|---|---|---|
| Diagnosis, imaging and staging | Mammogram, ultrasound, biopsy, and often MRI; tumour marker clip may be placed | 1 to 3 weeks |
| Chemotherapy before surgery (if advised) | Typically several cycles of intravenous treatment with periodic scans to monitor response | About 3 to 6 months, when used |
| Breast and lymph node surgery | Lumpectomy, oncoplastic reshaping or mastectomy, usually combined with sentinel node biopsy | Day surgery to 1–2 nights in hospital |
| Recovery before further treatment | Wound healing, arm and shoulder exercises, review of final pathology | 2 to 4 weeks |
| Radiotherapy (if advised) | Daily sessions over several weeks, or a shorter high-dose course depending on protocol | Usually starts 4 to 12 weeks after surgery |
| Ongoing therapy and follow-up | Hormone therapy, targeted therapy and regular clinical review and imaging | Often continues for 5 to 10 years |
